 Single Vial Peptides
Not enough evidence" is a shrug, not a clean bill of health
If you are a straight man and you have sex, the official chart does not have your back the way you think a health agency should.
In September 2021 the U.S. Preventive Services Task Force said screen sexually active women 24 and younger for chlamydia and gonorrhea, and screen women 25 and older if they are at higher risk. For men, the same document says the evidence is insufficient. An "I" statement. Not yes. Not no. We do not have enough studies, so we will not tell you to get tested.
That line is still sitting there. The CDC's screening page repeats it for men who have sex with women: insufficient evidence to screen heterosexual men who are at low risk. The Task Force vice chair, Michael Barry, said it out loud. There is not enough evidence to know whether screening men cuts complications or spread. They want more research.
Read that again. The answer for men is not "you are healthy." The answer is "we never finished the homework."
What the paper actually says
Race is not a category in that recommendation. The categories are sex, age, and sexual behavior.
Here is the split, in their words, not mine:
- Women who are sexually active and 24 or younger: screen. USPSTF, September 14, 2021, also printed in JAMA, 2021, volume 326, pages 949 to 956.
- Men, for those same two infections: evidence insufficient. Same document.
- Men who have sex with men: the CDC tells clinics to screen at least once a year at the body sites involved, and every 3 to 6 months if the risk is higher. CDC screening recommendations, pointing at the 2021 STI treatment guidelines.
- HIV: screen pretty much everybody 13 to 64 at least once. Straight men are included. That part is not a shrug. USPSTF HIV recommendation, 2019.
HIV screening is written for adults in general, and straight men are on that list. The hole is chlamydia and gonorrhea for men the chart calls low risk. Men who have sex with men get a separate CDC schedule, at least once a year, because those two infections show up more often there. Women get a clear yes. A lot of men get a shrug from the same agencies. That paperwork is not a reason to skip a test, and it is not a clean bill of health.
The hole is still indefensible as advice to a person. "We did not study you enough" is being used as the default. Meanwhile the same agencies will give women a clear yes. You can get chlamydia with no symptoms. You can hand it to a partner. Epididymitis is a real complication in men, and the big review still could not show that routine screening prevents it. Their conclusion was "come back later with better studies." Your crotch does not wait on a study section.
Do not outsource this to whoever is in the chair
People mash the FDA, the CDC, and the Task Force into one blob. This particular shrug is the Preventive Services Task Force. They say they are independent of the government. The CDC then copies the line onto the page doctors actually use.
Joe Biden was Vice President in 2014. Barack Obama was President. The 2014 recommendation already said the evidence was insufficient for men. Biden was President in September 2021, and that recommendation says it is consistent with 2014. In the years between, Donald Trump was President, and this line did not get rewritten into "screen men." Biden was in the building for both write-ups, first as vice president and then as president. He still did not author the page. The Preventive Services Task Force did, and they kept the same shrug. Agencies do change emphasis when leadership changes. This particular blank sat through more than one crew.
A blank from an agency is not a medical exam. If you have a new partner, more than one partner, a partner who has other partners, or a partner who just tested positive, you have a reason to test that does not need their permission. Ask for the urine test. Ask for HIV while you are there. If you have symptoms, that is not screening anymore. That is "go in."
Retatrutide is not the FDA selling a drug early
Reta is retatrutide. Eli Lilly is developing it. The FDA has not approved it. Lilly has said it plans to submit an application in the first quarter of 2027. A plan to file is not an approval.
Lilly did open a narrow door before that filing. On August 3, 2026, Lilly said some patients can apply for early access while the drug is still unapproved. AJMC reported that on August 5. The path grew out of one compassionate-use case in April 2026, a 79-year-old patient referred by an NIH clinician. Doctors then asked why their own patients could not get the same thing. Reported rules differ by outlet. One account says the patient has to be 18 or older, unable to join a trial, with refractory obesity and at least two serious complications, after the standard options were discussed. Reuters quoted a spokesperson saying the person had to have already failed the highest approved obesity dose. Doctors complained about silence and vague replies. That is Lilly choosing who gets an unapproved drug. It is not the FDA approving it, and it is not a product you can buy at a counter.
Lilly still says anything sold to the public outside its trials is not an approved medicine. The FDA has said retatrutide is not part of an approved drug and cannot be used in compounding.
Drug companies do pay the FDA to review applications. Those are user fees, under the law called PDUFA. People are right to hate how close the money sits. A fee for a review is still not a receipt that buys a yes, and it is not the FDA selling reta before the paperwork is even in.
The 2025 GLP cutoff did not stop the compounders
The FDA took tirzepatide off the shortage list in December 2024 and semaglutide off in February 2025. Copying those drugs under the shortage rule then had a wind-down. For tirzepatide, state pharmacies were told to stop around February 18, 2025, and bigger outsourcing facilities around March 19, 2025. For semaglutide, the dates ran to about April 22, 2025, and May 22, 2025. In September 2026 the Fifth Circuit left those shortage decisions standing.
The market did not treat the dates as the end. Between August and October 2025, University of Colorado researchers called 75 weight-loss clinics and med spas in West Virginia and Oklahoma. About 92% were still offering compounded semaglutide. About 87% were still offering compounded tirzepatide. A lot of the vials had an extra ingredient, often a B vitamin, which is the usual way a pharmacy claims the mix is not a straight copy. That study landed in JAMA Health Forum.
The FDA sent dozens of warning letters in September 2025 about the ads. In February 2026 it said it could seize product and go to court without another warning. In April 2026 it proposed kicking semaglutide, tirzepatide, and liraglutide off the bulk list that large compounders use, so a future shortage would not automatically reopen the factory door. As of fall 2026 that proposal was still a proposal. The letters and the deadlines did not clear the shelves. A narrow patient-specific exception still exists on paper. What the phone survey found was not narrow.
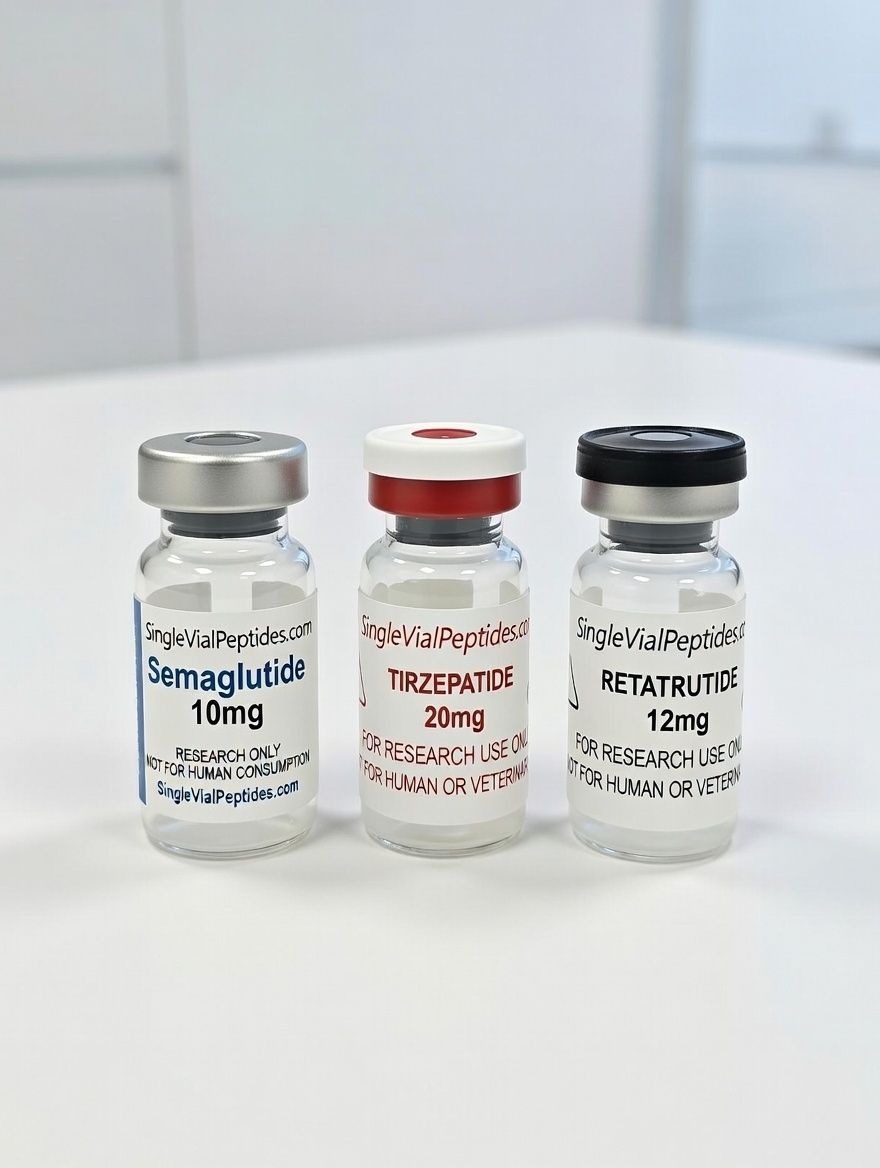
The research vials on this shop are not Lilly's drug and they are not an FDA approval. Research use only. 21 and older. Not for people or animals.
We are not a clinic. This is not a diagnosis and it is not medical advice. It is a reading of their own papers, and a suggestion that you treat "evidence insufficient" as their problem, not as your all-clear.
Sources, if you want to argue with the page instead of with a summary:
- USPSTF final recommendation, chlamydia and gonorrhea, September 14, 2021
- USPSTF announcement the same day
- CDC STI screening recommendations
- USPSTF HIV screening
- Lilly, what to know about retatrutide
- AJMC, Lilly expands retatrutide access amid doctor pushback, August 5, 2026
- Reuters, August 3, 2026
- Drug Topics, compounded GLP-1s still offered after the shortage, July 20, 2026
- Pharmacy Times, FDA proposal on bulk compounding of semaglutide, tirzepatide, and liraglutide
Research vials. 21 and older. Not for people or animals. Not medical advice.